15 Questions to Ask Before Knee Replacement Surgery

Ask how many knee replacements your surgeon performs each year; a specific number is a good sign.
The pre-operative consultation for knee replacement is not just a formality before scheduling. It is the moment when a patient who arrives with incomplete information can leave with everything they need to make an informed decision — and when a patient who does not ask the right questions may leave with a planned operation they do not fully understand.
Most patients arrive at a consultation with general questions ("Will it hurt?") rather than specific ones. This guide gives you the specific questions that reveal whether you are in the right hands, whether surgery is genuinely indicated, and whether your expectations match what the procedure can actually achieve.
Questions About Whether Surgery Is the Right Choice Now
1. Is conservative management genuinely exhausted for my knee?
This is the most important question in the consultation, and it is the one most patients are afraid to ask.
A good answer includes: honest assessment of whether physiotherapy has been consistently performed (not just prescribed), whether weight management has been meaningfully attempted, whether the arthritis grade genuinely indicates that further conservative management has limited remaining potential. An answer that dismisses this question, or that recommends surgery at the first visit without specifically reviewing what conservative management has been tried, is a concern.
2. What is the grade of arthritis in my knee?
The answer should reference the X-ray findings specifically: which compartment (medial, lateral, patellofemoral), how much joint space remains, whether there are osteophytes (bone spurs), and whether alignment is affected. Grade I to II arthritis with significant remaining joint space should rarely be progressing to knee replacement without a clear explanation of why conservative management has failed.
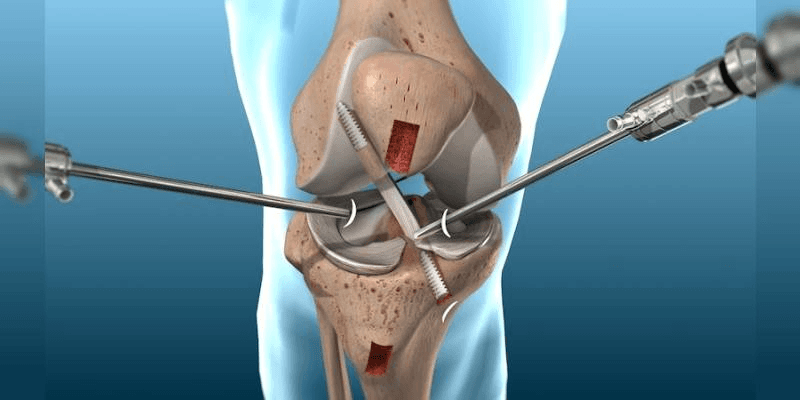
3. Could partial knee replacement (UKR) work for my knee?
If arthritis is predominantly in one compartment (usually medial), partial replacement preserves the healthy parts of the joint, offers better deep flexion, and has equivalent long-term survival in appropriately selected patients. If the surgeon has not raised this as an option, ask why total replacement is indicated rather than partial.
Questions About the Surgeon and the Procedure
4. How many knee replacements do you perform per year?
Surgical volume is the strongest evidence-based predictor of outcome quality. The answer should be a specific number — not a vague "many." High-volume specialists performing 100-plus procedures per year consistently produce better alignment accuracy, lower complication rates, and better patient satisfaction than low-volume surgeons.
5. Who will actually perform my surgery?
In large hospitals, the named senior surgeon may be supervising while a registrar or junior consultant performs the procedure. This is not inherently wrong — training is how surgeons develop — but a patient is entitled to know who will hold the instruments, and to make an informed decision about whether they accept this.
6. Will you be using robotic guidance, and if so, which system?
If the surgeon has robotic access, confirm it for your case — not just that the hospital has the system. If robotic surgery is not being used, ask why — the answer should be a specific clinical reason, not a vague "it is not necessary." For patients under 65, or for patients with significant deformity, the alignment accuracy advantage of robotic guidance is clinically meaningful.
7. Which implant will be used, and why?
The answer should include the implant type, the fixation method (cemented or cementless), and the bearing surface material. Specifically, confirm the tibial insert is highly cross-linked polyethylene (HXLPE) — the current standard bearing surface with substantially better wear resistance than conventional polyethylene.
Questions About Your Specific Expected Outcomes
8. What range of motion should I expect after surgery?
Total knee replacement typically achieves 110 to 120 degrees of flexion. Partial replacement and robotic-assisted surgery may achieve more. For Indian patients, this translates directly to: will I be able to sit cross-legged? Use an Indian toilet comfortably? Sit on a low charpoy? The surgeon's answer should be specific to the procedure being planned and your specific anatomy.
9. What activities will I be able to do — and what will I not be able to do?
After total knee replacement, walking, cycling, swimming, and social sport are compatible with implant longevity. Running, jumping sports, and deep squatting under load are not recommended. If you have specific activity goals — returning to cricket, badminton, yoga, farming — raise them explicitly and get a specific answer about their feasibility.
10. What pain level should I expect after surgery, and for how long?
A good answer distinguishes between immediate post-operative pain (managed with medication, resolves over weeks) and the longer discomfort of physiotherapy (expected, appropriate). It also sets realistic expectations: the knee continues improving for 6 to 12 months. The specific medication plan for pain management at home should be discussed.
Questions About the Hospital and Peri-Operative Care
11. How long will I be in hospital?
Standard total knee replacement: 3 to 5 days. Bilateral simultaneous: 5 to 7 days. Partial replacement: 2 to 3 days. If the answer is significantly different from these, ask why.
12. What does Day 1 after surgery look like?
The answer should include: when physiotherapy starts (Day 1), when you first attempt standing and walking (Day 1), what exercises you will do in hospital, and what the discharge criteria are. A surgeon who has a clear, structured answer demonstrates that their hospital has a defined post-operative protocol.
13. What blood clot prevention protocol will be used?
DVT (deep vein thrombosis) is the most common serious complication after knee replacement. The standard prevention includes blood-thinning tablets from Day 1 (for 2 to 4 weeks), compression stockings, early walking, and adequate hydration. A surgeon who does not have a clear protocol answer for this is a concern.
Questions About the Recovery
14. When can I drive, and when can I go back to work?
Right knee replacement: driving typically at 6 to 8 weeks (when you can perform emergency braking). Left knee: slightly earlier for automatic transmission vehicles. Desk work: 6 to 8 weeks. Standing work: 8 to 12 weeks. These timelines should be discussed specifically.
15. What should I prepare at home before surgery?
A good surgeon will specifically advise on:
- Raised toilet seat (essential before discharge — not optional)
- Bed height (should not require significant hip and knee flexion to get into)
- Trip hazards to remove
- Items to keep within reach without bending
- Family or carer availability for at least 2 to 4 weeks
A surgeon who sends you home unprepared for the post-operative environment has not completed the pre-operative process.
What Good Answers Look Like — and What Doesn't
Signs of a high-quality consultation:
- Specific answers to volume, implant, and robotic questions
- Explicit discussion of alternatives before agreeing on surgery
- Clear, structured explanation of the recovery process
- Time for your questions — not rushed
- Honesty about what surgery cannot achieve (running, deep squatting)
Signs of a consultation to be cautious about:
- Surgery recommended within 5 minutes without examination
- No discussion of alternatives
- Vague answers about volume ("many") or implant ("the best one")
- Dismissiveness about a second opinion
- Overpromising on outcomes ("you'll be back to normal in 6 weeks")
The information in this guide is the framework. Your consultation with Dr. Ankur Singh at Renew Orthopedic Clinic, Sector 47 Noida, will use this framework with the specifics of your knee — your arthritis grade, your alignment, your functional goals, your medical history — to produce an answer that is genuinely yours.
To book: call the number listed on this website.
Frequently Asked Questions
Is it rude to ask my surgeon these questions? No. A confident, ethical surgeon welcomes specific, informed questions from patients. A surgeon who is defensive or dismissive about these questions is communicating something worth knowing before you make your decision.
Should I bring someone with me to the consultation? Yes — strongly recommended. A family member or friend who can listen, note key information, and ask follow-up questions substantially improves how much useful information patients retain from consultations. They can also help raise questions you might forget under the stress of the appointment.
Dr. Ankur Singh | Knee Replacement Specialist Noida | Questions Before Knee Replacement India | Sarvodaya Healthcare Noida | Renew Orthopedic Clinic Sector 47 Noida
Medical Disclaimer
The information provided on this website is for educational purposes only and should not be considered as medical advice. Please consult Dr. Ankur Singh or a qualified healthcare professional for personalized medical guidance.
Share this blog:
 Copy




.jpg)