PCL Injury: Why It's Completely Different from ACL — And Why Most Patients Get It Wrong

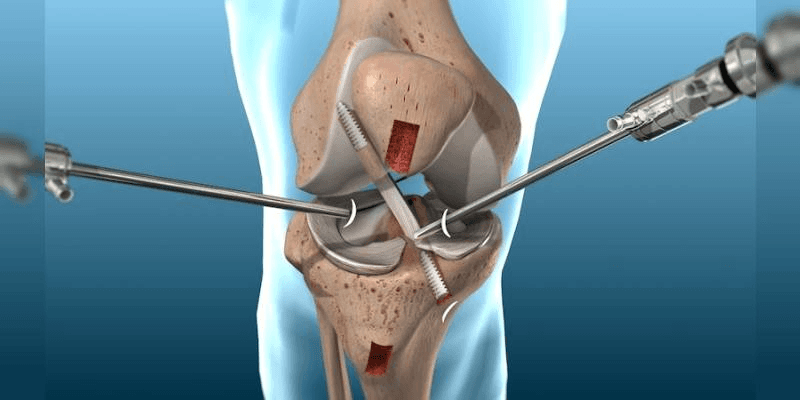
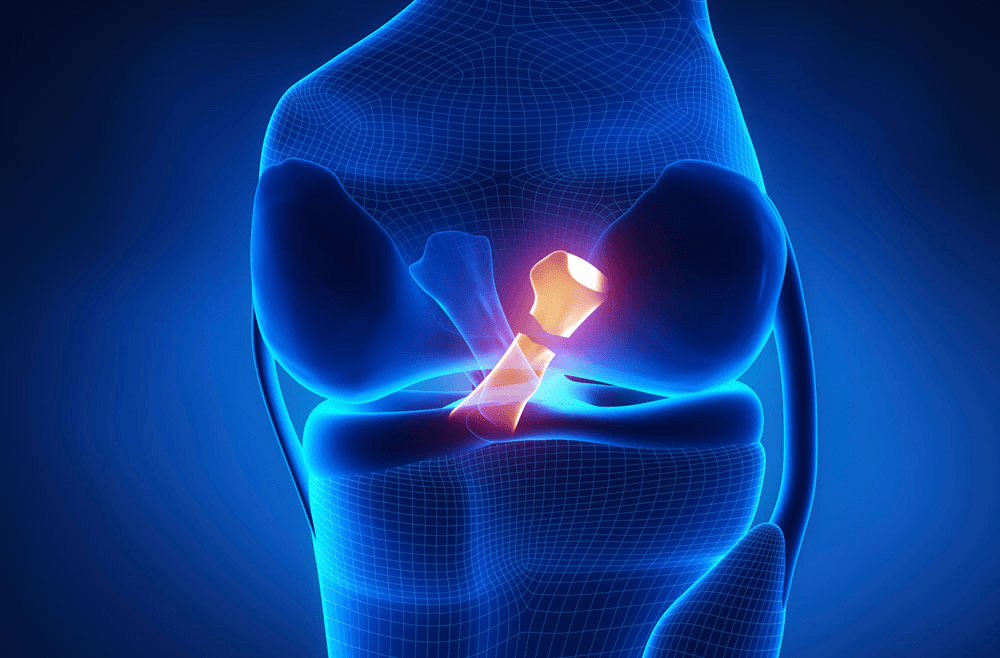
A diagram is shown, illustrating PCL injury on the knee.
The ACL gets almost all the attention in Indian sports medicine. It is the injury that cricket commentators reference, that gym enthusiasts fear, and that most Indians have at least some awareness of. When someone injures their knee in a sport and it swells dramatically, the immediate assumption is ACL.
The PCL — the posterior cruciate ligament — is a different structure, with different biomechanics, a different injury mechanism, different consequences when torn, and a completely different management philosophy. Most importantly, it is significantly more common than most patients realise, particularly in the Indian context — and it is routinely overtreated, mismanaged, or managed using ACL protocols that do not apply.
Understanding the PCL is genuinely useful for Indian patients, athletes, and the families of two-wheeler riders.
What the PCL Does
The knee has four major ligaments. The ACL (anterior cruciate ligament) prevents the shin bone (tibia) from sliding forward on the thigh bone (femur). The PCL (posterior cruciate ligament) prevents the opposite: the tibia sliding backward on the femur.
The PCL is actually the stronger of the two cruciate ligaments — it is wider, more robust, and has a better blood supply than the ACL. This has significant implications for healing.
Under normal circumstances, the PCL resists forces that push the tibia backward — the "dashboard mechanism" where a bent knee strikes a hard surface with the force directed from front to back. It also resists hyperflexion of the knee (knee bent beyond its comfortable maximum range).
The Most Common Cause in India: Dashboard Injury
In India, one injury mechanism accounts for a disproportionate share of PCL tears compared to Western populations: the dashboard injury.
When a two-wheeler rider or car passenger is involved in a front-end collision, the bent knee may strike the instrument panel, handlebars, or the front of the vehicle. The force is applied to the front of the shin with the knee bent — pushing the tibia directly backward. This is the classic dashboard mechanism, and it is one of the most reliable mechanisms for PCL injury.
Given India's position as the world's largest two-wheeler market — with hundreds of millions of motorcycles and scooters on the roads — the number of Indians who sustain dashboard-mechanism PCL injuries annually is very large. Many of these injuries are misdiagnosed as contusions (bruises), ACL injuries, or "general knee ligament injuries" without the PCL being specifically assessed.
Other mechanisms:
- A direct fall onto a bent knee with the foot plantarflexed (toes pointed down) — common in sports falls
- Hyperflexion injuries in sports (deep squat position with sudden loading)
- High-energy sports collisions (football, kabaddi)
How PCL Injury Differs from ACL: The Key Clinical Distinctions
1. The Bleeding and Swelling Pattern
ACL tears almost always produce immediate, rapid swelling (haemarthrosis) — within 2 to 4 hours of injury. The knee fills with blood from torn vessels at the ACL's attachment sites.
PCL tears are more variable. Some cause significant swelling; others produce surprisingly little swelling despite a complete ligament tear. A patient with a significant PCL tear who has minimal swelling may dismiss the injury as a bruise — missing the structural damage that has occurred.
2. The Pain Location
ACL injury pain is usually felt inside the knee, diffusely. PCL injury pain is often felt at the back of the knee (posterior) — where the PCL attaches to the back of the tibia. Posterior knee pain after a dashboard-type mechanism should immediately raise PCL suspicion.
3. The Instability Pattern
ACL instability: the knee gives way during cutting, pivoting, and sudden direction changes. The instability is rotational and occurs during dynamic activities.
PCL instability: the tibia sags backward relative to the femur when the knee is at 90 degrees of flexion. In mild PCL injuries, many patients describe no clear instability during daily activities — the knee "works" for most purposes but may feel vaguely wrong on stairs or when going from sitting to standing.
The "posterior drawer test" — where the examiner pushes the shin backward relative to the thigh with the knee at 90 degrees — is the clinical test that specifically assesses PCL integrity. It is positive (abnormal posterior movement) with PCL injury and normal with ACL injury.
4. The Healing Potential
This is the most important clinical distinction: the PCL heals much better than the ACL.
The ACL is intra-articular (inside the joint) and avascular (no direct blood supply) — which is why it cannot heal itself when completely torn. An ACL tear without reconstruction produces permanent instability.
The PCL has a better vascular supply and, in many cases, retains continuity even in partial tears. Isolated PCL injuries — particularly Grade I and Grade II tears — have documented healing rates with conservative management that are vastly better than ACL injuries. Multiple studies show that 50 to 80 percent of isolated PCL injuries managed conservatively achieve functional stability and return to activity without surgery.
This is the fundamental reason that PCL management philosophy differs from ACL management philosophy: many PCL tears that would be automatically reconstructed if they were ACL tears should actually be managed non-surgically.
PCL Grading
Grade I (mild sprain, ligament intact):
Some fibres stretched, ligament structurally intact. The posterior drawer test shows 0 to 5 mm of abnormal posterior tibial movement. These always heal with conservative management. Return to sport in 2 to 4 weeks.
Grade II (partial tear):
Significant portion of fibres torn, ligament partially disrupted. Posterior drawer shows 5 to 10 mm of abnormal movement. Most heal with conservative management and a structured rehabilitation programme. Surgery is rarely indicated for isolated Grade II PCL injuries.
Grade III (complete rupture):
Complete tear of the PCL. Posterior drawer shows more than 10 mm of abnormal posterior tibial movement. Management of isolated Grade III PCL injuries remains controversial in sports medicine literature — the consensus from a 2025 Delphi study involving 90 international orthopedic experts was that isolated Grade III tears often still do not require surgical reconstruction, particularly in non-athletes or lower-demand patients.
Surgery is more clearly indicated for Grade III PCL injuries when:
- Combined with other ligament injuries (ACL, MCL, posterolateral corner — a "multi-ligament knee injury")
- The patient is a high-level athlete with specific rotational and stability demands
- Conservative management has failed to restore adequate function at 3 to 6 months
Conservative Management: What It Involves
For the majority of PCL injuries — isolated Grade I, II, and many Grade III — conservative management with structured physiotherapy produces excellent outcomes.
Phase 1 (weeks 1 to 4): Protection and pain management
- Brace or functional support to prevent excessive posterior tibial sag
- Physiotherapy focusing on quadriceps activation (the quadriceps is the dynamic restraint that compensates for PCL deficiency by actively preventing posterior tibial translation)
- Avoid deep knee flexion (past 90 degrees) and hamstring-dominant exercises in this phase — hamstring contraction pulls the tibia backward, stressing the healing PCL
Phase 2 (weeks 4 to 12): Strengthening
- Progressive quadriceps strengthening: leg press, wall squats, step-ups
- Hip and core strengthening
- Proprioceptive training (balance work) — PCL injury disrupts joint position sense that must be rehabilitated
- Cycling (stationary, low resistance) from around week 6
- Introduction of hamstring work at lower loads as the PCL heals
Phase 3 (months 3 to 6): Return to function
- Sport-specific training
- Running, cutting, pivoting activities progressively reintroduced
- Return to sport criteria: functional strength symmetry, confidence, sport-specific movement quality
PCL Reconstruction: When Surgery Is the Right Decision
When conservative management is genuinely insufficient — high-grade injuries in high-demand athletes, multi-ligament injuries, or patients who remain significantly functionally limited at 3 to 6 months — PCL reconstruction is performed arthroscopically.
PCL reconstruction is technically more complex than ACL reconstruction due to the PCL's position behind the knee and its proximity to important vascular structures. The posterior tibial tunnel — where the graft is anchored — requires precise drilling to avoid the popliteal neurovascular bundle. This is a procedure where surgical experience in PCL-specific technique matters significantly.
Assessment for PCL Injury in Noida
Dr. Ankur Singh sees PCL injuries as part of his knee and sports medicine practice at KDSG Superspeciality Hospital in Greater Noida. The evaluation includes clinical examination (posterior drawer test, posterior sag sign), MRI to confirm ligament status and assess for concomitant injuries, and discussion of the appropriate management pathway based on the injury grade, patient demands, and functional assessment.
If you have had a two-wheeler accident involving knee trauma, a contact sports knee injury, or a fall on a bent knee — and your knee pain is primarily at the back of the knee with limited clear instability but an uncertain diagnosis — a specialist assessment for PCL injury is worth pursuing.
To book at Renew Orthopedic Clinic, Sector 47 Noida, call the number listed on this website.
Frequently Asked Questions
Is PCL injury more or less serious than ACL injury?
Differently serious rather than more or less. ACL injuries almost always require reconstruction for athletes returning to cutting sports. PCL injuries have significantly better healing potential and many can be managed conservatively. Multi-ligament injuries involving both ACL and PCL are more complex than either in isolation.
Why does my physiotherapist emphasise quadriceps exercises for my PCL injury?
The quadriceps actively prevents the tibia from sagging backward — which is what the PCL does passively. In PCL-deficient knees, a strong quadriceps is the most important compensator for ligament deficiency. Quadriceps strengthening is therefore the cornerstone of PCL rehabilitation in a way it is not for other knee injuries.
How long before I can ride a two-wheeler after a PCL injury?
For Grade I injuries managed conservatively: 3 to 6 weeks depending on pain and confidence. For Grade II injuries: 6 to 12 weeks. For Grade III injuries or those requiring surgery: 4 to 6 months minimum. A two-wheeler requires dynamic knee control under load — assess readiness honestly.
Dr. Ankur Singh | Knee Specialist Noida | PCL Injury Treatment Noida | Sports Medicine Greater Noida | KDSG Superspeciality Hospital | Renew Orthopedic Clinic Sector 47 Noida
Medical Disclaimer
The information provided on this website is for educational purposes only and should not be considered as medical advice. Please consult Dr. Ankur Singh or a qualified healthcare professional for personalized medical guidance.
Share this blog:
 Copy



.jpg)

